Recent lifting belongs in the context of a liver enzyme result
By Mr.Apps · Oct 26, 2026
Category:Energy

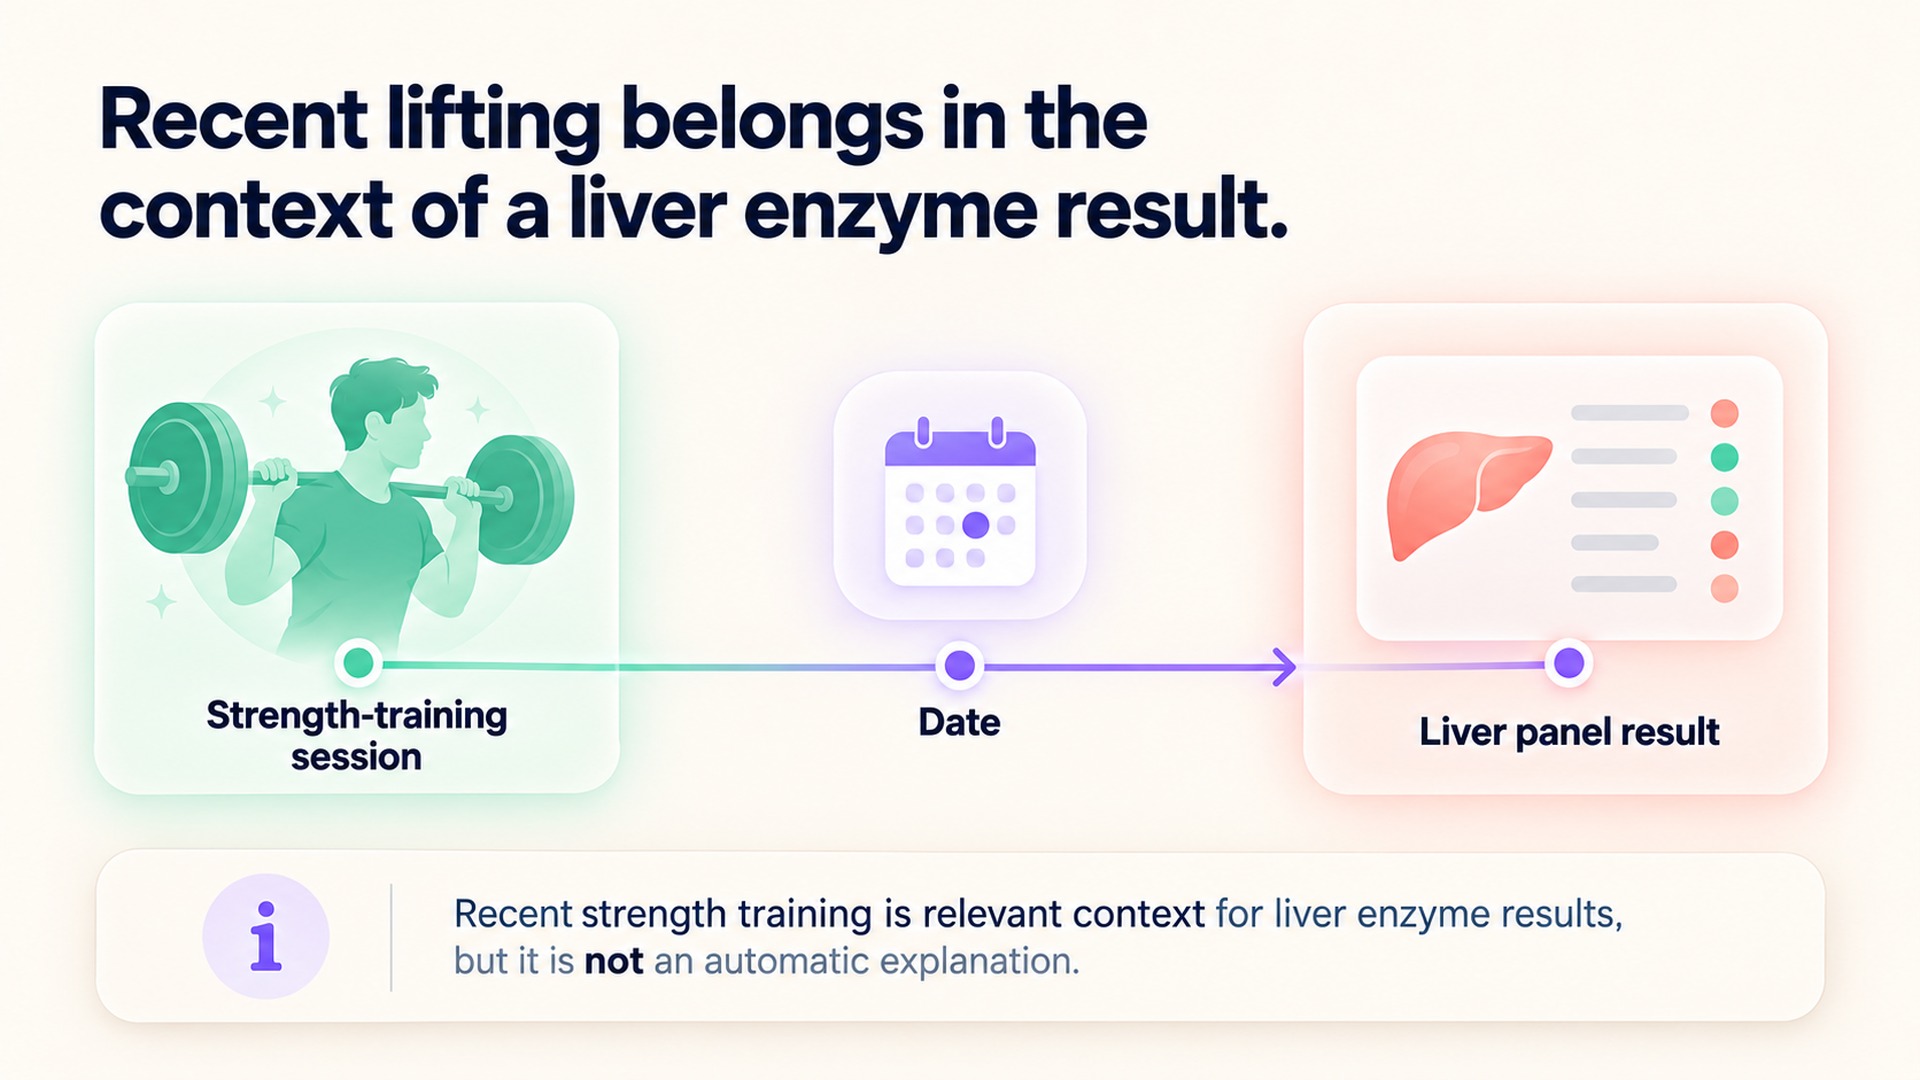
A liver enzyme result can be difficult to interpret without knowing what happened before the blood draw. Recent strenuous lifting may be relevant because muscle tissue can affect some enzymes measured on a liver panel. That fact is useful context, but it is not an automatic explanation for an abnormal result. A clinician still needs to consider the exact tests, symptoms, timing, medicines, medical history, and whether other findings point toward a liver or muscle source.
The goal is to preserve the exercise history without using it to dismiss a result. AST and ALT are often discussed as liver enzymes, but AST is also present in muscle and other tissues. CK is a muscle enzyme that may add information when muscle injury is being considered. None of these values should be treated as a workout score or a diagnosis on its own. I would record the date and type of recent lifting, then ask how that information fits the full panel.
What a liver panel shows
A liver panel may include enzymes and other measurements such as bilirubin. These tests do not all answer the same question. Some values can rise when liver cells are injured, while others help assess bile flow or related functions. The liver function test overview describes the different tests that may be included and why results are interpreted together.
ALT is found mainly in the liver, while AST is found in the liver and other tissues, including muscle. An elevation can be a signal worth investigating, but it does not tell the cause by itself. The ALT blood test guide explains that an elevated ALT may be associated with liver injury or disease, while the AST test overview describes the enzyme measurement as part of a broader assessment. The clinician considers the pattern, degree of change, and other tests rather than reading one enzyme as a complete diagnosis.
Recent exercise belongs in that context because muscle stress can affect laboratory values. A small study of healthy men who were not accustomed to weightlifting found that several blood chemistry measures, including AST, ALT, CK, and myoglobin, increased after an intensive session. Its participants and protocol were limited, so it does not establish a universal waiting period or explain every abnormal result. The study of muscular exercise and liver tests supports noting recent lifting while preserving the limits of that evidence.
Why muscle activity can matter
Muscle tissue contains enzymes measured in blood testing. After unfamiliar or strenuous exercise, muscle stress can contribute to changes in CK and, in some circumstances, AST and ALT. The timing and pattern vary. The amount of weight lifted alone does not predict what a laboratory value should be, and a person can have an abnormal result for a reason unrelated to exercise. That is why the training session should be recorded as context rather than used to assign a cause.
CK can help the clinician consider whether muscle tissue may contribute to a pattern, but it does not independently prove the source. A creatine kinase test overview explains that CK is measured in a blood sample and interpreted with other clinical information. If a liver panel and CK are both reviewed, the clinician may consider their relationship alongside symptoms and the rest of the report. A result should not be simplified to “muscle” or “liver” without that assessment.
Reference intervals are not universal cutoffs for every person or every laboratory. They are produced for a particular test method and are used alongside the clinical setting. A value just outside an interval may need a different response from a large or persistent change, but the size alone still does not identify the source. Comparing a current result with an older one is more informative when both were measured by the same laboratory and when the exercise history is known.
The full pattern matters as well. Other components of the liver panel may point toward a different question than AST or ALT alone. A clinician may consider bilirubin, alkaline phosphatase, GGT, CK, symptoms, and relevant history together. Not every person needs every additional test; the choice depends on the reason the panel was ordered and what the initial results show. A single value should not be treated as the complete story.
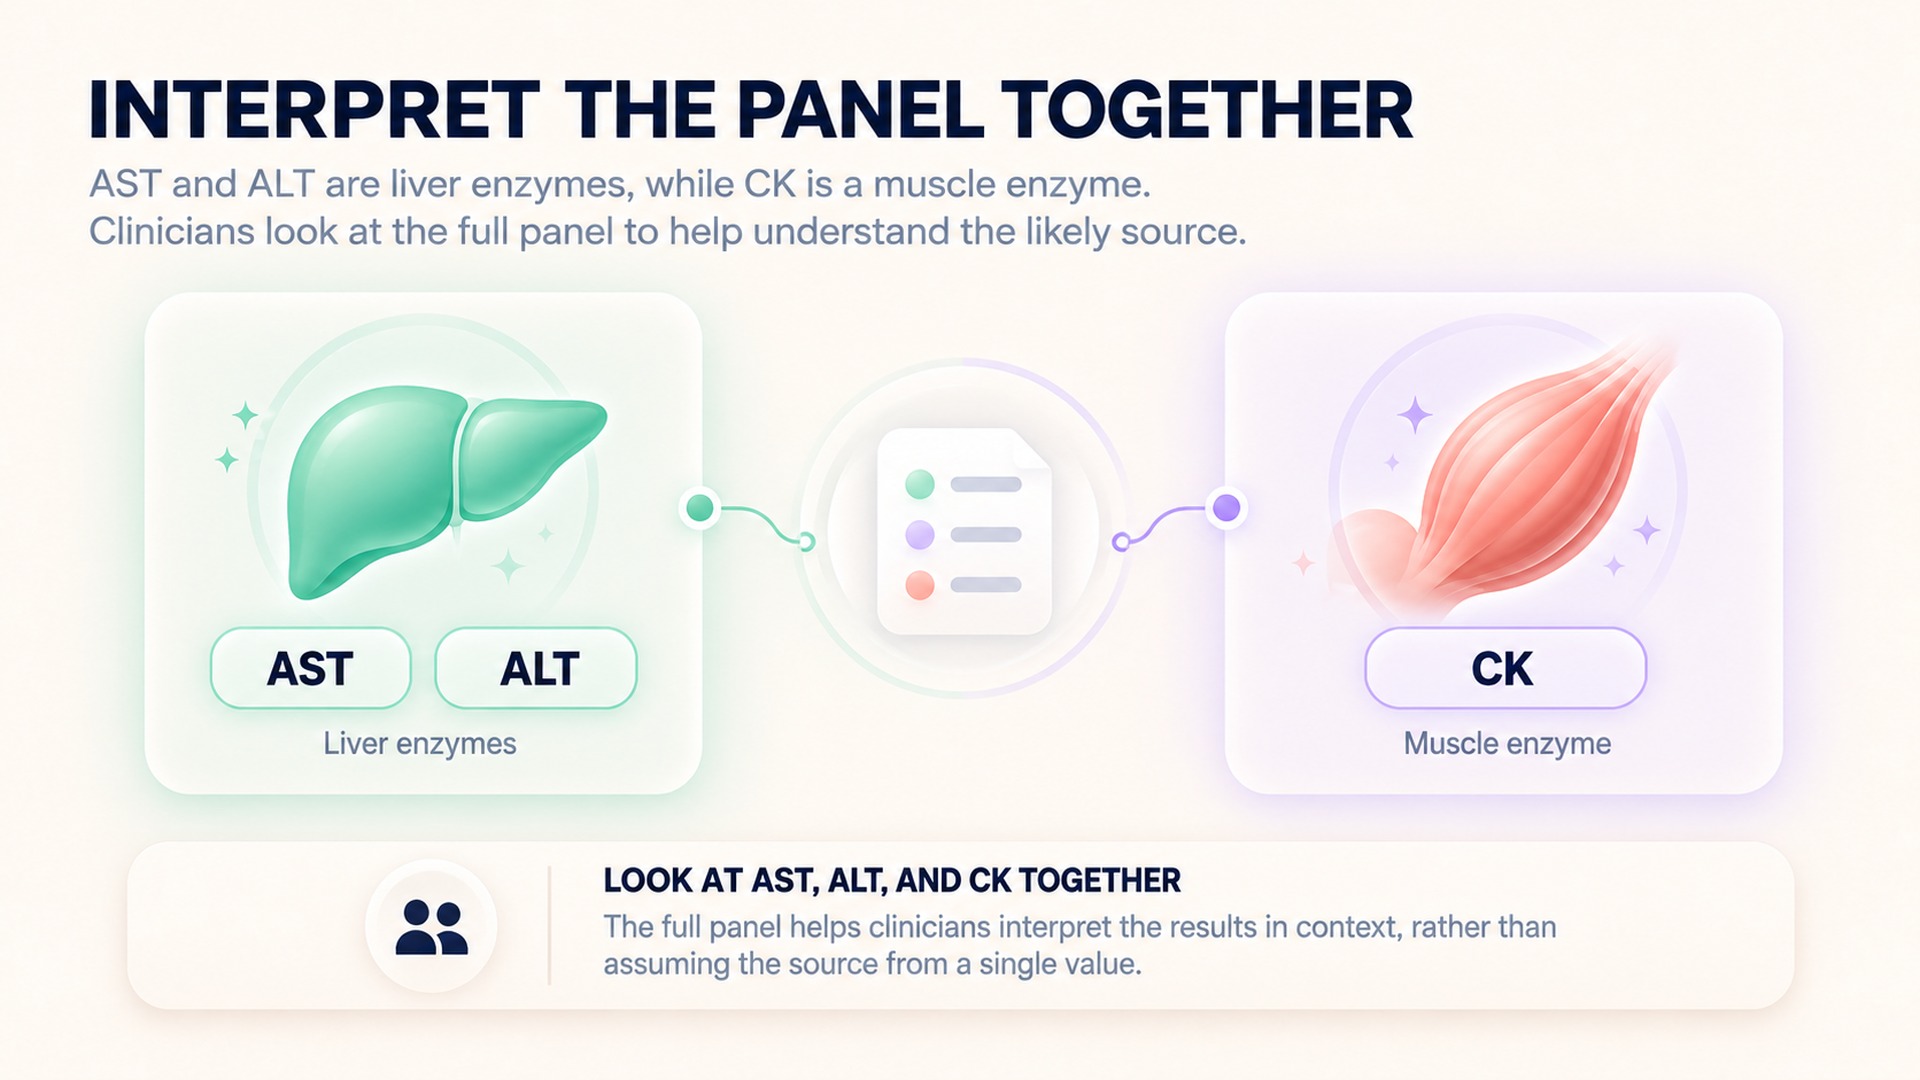
A guideline for evaluating abnormal liver chemistries emphasizes that the full pattern matters. The clinical guideline on abnormal liver chemistries describes how clinicians assess enzyme results and other relevant findings. The guidance is not a self-diagnosis tool. It supports the principle that a single elevated value should be interpreted in relation to the patient's history and the other measurements on the panel.
The evidence about strenuous exercise also has limits. One small study in a selected group cannot predict the response of every person, type of exercise, or test method. It shows why the history belongs in the conversation, not that every abnormal liver result after lifting has the same explanation. A clinician may decide to repeat a panel under specified conditions, evaluate other causes, or take another step based on the broader record.
When discussing the result, ask which parts of the panel were abnormal, whether recent exercise could affect any of them, and what findings would make a repeat test or additional evaluation appropriate. The answer may differ depending on symptoms and medical history. Keeping the exact questions with the result makes follow-up more focused and reduces the chance that a plausible workout connection will be mistaken for a confirmed cause.
Keep the training timeline with the report
Write down the date of the last strenuous or unfamiliar lifting session and the date of the blood draw. Include the type of activity and whether it involved a major change in load, volume, or movement. Note muscle soreness, weakness, pain, or other symptoms, including when they began and whether they are improving or worsening. These details allow a clinician to decide whether the exercise history is relevant and whether more evaluation is needed.
Preserve the complete laboratory report. Keep the names of the tests, exact values, units, reference intervals, collection date, and laboratory together. If the test was repeated, record whether it was done at the same lab and whether the exercise conditions were similar. A result copied without its date or reference range is much harder to interpret.
That context can guide comparison. A concise timeline can help prevent a common mistake in this setting: comparing a blood draw after a demanding session with a baseline collected during a different routine and treating the difference as a direct measure of change in the liver. The timeline does not diagnose anything, but it gives the clinician a chance to decide whether the samples are meaningfully comparable and what other context should be reviewed. The exercise record should sit beside the report, not replace it.
Medicines, supplements, alcohol use, recent illness, and other health conditions may also matter, depending on the clinical question. Provide an accurate list and follow instructions from the care team. Do not stop a prescribed medicine or delay follow-up because lifting seems like a plausible explanation. If a clinician recommends repeating a test, ask whether the same panel should be used, how to prepare, and what activities to avoid, if any. There is no single pre-test restriction that applies to every patient and every situation.
Avoid turning context into reassurance
Knowing that recent exercise can affect some results should make interpretation more careful, not less. An abnormal liver enzyme value may still require evaluation even when it follows a workout. The clinician may consider liver-specific markers, CK, symptoms, medical history, and repeat results to determine what explanation is most likely. An exercise history is one part of that process, not a reason to skip it.
A consumer recovery score or activity graph can help show when a training session occurred, but it cannot determine the source of a liver panel change. A low score does not diagnose muscle injury, and a normal score does not rule out a liver condition. Keep app estimates separate from laboratory findings and let the care team interpret both within their limits. For broader context on health measurements, see this overview of interpreting health app biomarkers.
Questions people ask
Can weightlifting raise AST or ALT?
It can affect some laboratory values, including AST and ALT, in some circumstances. The effect depends on the activity, timing, and person. Recent lifting is relevant context, but it does not automatically explain an abnormal result.
Does a high CK prove that a liver panel result came from muscle?
No. CK can add information about muscle involvement, but it does not by itself establish the source of AST or ALT. A clinician interprets it with the full panel, symptoms, history, and timing.
Should someone avoid lifting for a fixed number of days before blood work?
There is no single waiting period that applies to everyone. Follow the ordering clinician's or laboratory's instructions. If the test is already complete, record the activity date and share it during the review.
*This article is for informational purposes only and is not a substitute for professional medical advice, diagnosis or treatment.*
Sources:
National Library of Medicine·National Library of Medicine·National Library of Medicine·British Journal of Clinical Pharmacology·American College of Gastroenterology·National Library of Medicine
Related articles

Keep the kidney function equation beside an eGFR trend
Learn why a change in the eGFR equation can shift a reported estimate without an equivalent biological change. See what to record beside each value so a trend can be interpreted with its method and clinical context.

Creatine kinase after exercise requires symptoms and timing
Learn why recent exercise, test timing, and symptoms all matter when a creatine kinase result is reviewed. See why CK is a clinical marker rather than a training target and when unusual symptoms need prompt attention.

Normal oxygen saturation does not establish a normal hemoglobin level
A pulse-oximeter percentage estimates how much available hemoglobin is carrying oxygen, while a blood count measures hemoglobin amount. Learn why one reassuring reading cannot replace the other test or a clinical review.

A raised CRP result cannot identify the source of inflammation
A raised CRP can signal inflammation, but it cannot identify where the process is or what caused it. Learn why standard CRP and high-sensitivity CRP serve different purposes and need clinical context.

When a vitamin B12 result needs a methylmalonic acid check
Learn why a clinician may consider methylmalonic acid when a vitamin B12 result leaves a question unresolved. See how kidney function, symptoms, medicines, and other tests shape interpretation.

Reading TSH and free T4 together in a fatigue review
Learn what TSH and free T4 contribute to a fatigue review and why the two results need clinical context. See how symptoms, medicines, timing, and prior results help keep a lab value in its proper role.

Why Metabolic Energy Efficiency and Daily Energy Are Different Concepts
Metabolic energy efficiency describes processes involved in handling fuel, while a daily energy score is usually a separate app estimate about patterns such as sleep, activity, and recovery. Similar wording does not mean the two measures track the same thing.

Why a Monthly Metabolic Trend Cannot Explain One Meal
A monthly metabolic trend summarizes signals across a longer window and cannot identify what one meal did to glucose or insulin. Read it as a broad estimate, keep meal notes in their proper context, and use clinical testing for medical questions.

How Charging Gaps Break a 24-Hour Energy Timeline
Removing a wearable to charge creates a period when the device may not record the signals used by an energy model. A 24-hour timeline should mark that gap instead of treating it as neutral or connecting the surrounding values as continuous measurement.

How to Compare Energy Drain Across Days With Different Starting Scores
The ending value alone can hide how much an energy score changed during the day. Compare the start, decline, timing and data coverage on the same scale before interpreting differences between days.